

Diabetes and Strength Training: What Changes in the Gym?
I currently train several clients with diabetes myself, and the practical implications can be very different from one person to the next. Someone with well-managed type 2 diabetes may need very little adaptation to their training at all. Someone with type 1 diabetes using insulin has an entirely different set of things to think about. Another person may have diabetes as part of a wider medical condition, with that condition being more relevant to how we train them than the diabetes itself.
So when somebody tells us they have diabetes, the question isn’t simply whether they can exercise. We need to know what type of diabetes they have, how it is managed, what medication they use and whether there is anything else going on that affects how they should train.
Type 1 and type 2 diabetes aren’t the same thing
Type 1 diabetes is an autoimmune condition. The immune system attacks the cells in the pancreas which produce insulin, meaning the body can no longer produce enough of it. People with type 1 diabetes therefore need insulin to manage their blood glucose.
Type 2 diabetes is different. The body becomes resistant to the effects of insulin and, over time, may also become less able to produce enough insulin to meet its needs. It can be managed in different ways depending on the individual, including changes to diet and activity levels, weight loss, medication and, for some people, insulin.
That distinction matters when we start talking about exercise.
For somebody with type 1 diabetes, training has to be considered alongside insulin, food and blood glucose. Exercise can reduce blood glucose, including for some time after a session, while harder or more explosive forms of exercise can sometimes cause glucose to rise temporarily instead.
That doesn’t mean somebody with type 1 diabetes needs a particularly gentle training programme. People with type 1 diabetes can strength train, play sport and train seriously. The important bit is understanding how that individual’s blood glucose responds and making training fit around the management plan they already have in place.
Modern continuous glucose monitors can make this considerably easier for many people these days, because they can see what their glucose is doing before, during and after training. They remove a lot of the guesswork and potential for getting things badly wrong.
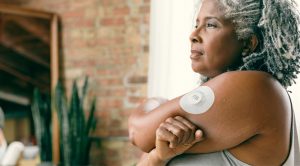
Modern real-time glucose monitors have been a game changer for clients wanting to strength train and worry less during the sessions
From a coaching point of view, we want to know that somebody uses insulin, what normally happens to their blood glucose when they exercise and what their usual strategy is if their glucose drops. We should also recognise the signs of hypoglycaemia and know what that individual normally uses to treat it.
What we don’t do is start telling somebody how much insulin to take or how to change their medication. That belongs with their diabetes team, not a PT.
Mark B, TYPE 1
“Once we’d worked out what tends to happen to my glucose during a session, training became much easier to plan. I don’t need a completely different workout. I just need to know what’s happening and be prepared for it.”
Type 2 diabetes and strength training
The conversation around type 2 diabetes is slightly different.
One of its defining features is insulin resistance. The body is producing insulin, but isn’t responding to it as effectively as it should.
Physical activity can improve insulin sensitivity, and resistance training is useful because muscle plays a major role in using glucose. Regular strength training can improve blood glucose management as well as strength, physical function, muscle mass and cardiovascular health.
Current diabetes exercise guidance doesn’t treat cardio as the only useful form of exercise. The American Diabetes Association, for example, recommends resistance exercise two or three times per week for adults with both type 1 and type 2 diabetes. Even our own NHS recommends resistance training for diabetics.
That becomes increasingly relevant as we get older. Maintaining muscle is useful for everybody, but if somebody already has problems with insulin sensitivity, allowing muscle mass and general physical activity to steadily decline certainly isn’t going to improve the situation.
There is another important point here too. Exercise can be worthwhile for somebody with type 2 diabetes even if they don’t lose a dramatic amount of weight.
For people carrying excess bodyweight, weight loss can substantially improve type 2 diabetes and, for some, significant weight loss can result in remission. There are now NHS programmes specifically built around this approach.
But that doesn’t mean every person with type 2 diabetes should automatically be put on a weight-loss programme, and it certainly doesn’t mean exercise has failed if somebody doesn’t lose several stones.
Getting stronger, preserving or gaining muscle, becoming fitter and being more physically active are worthwhile outcomes in their own right.
Katie, TYPE 2
“When I started, losing weight was part of the reason I wanted to train, but getting stronger became just as important. My training isn’t really about ‘having diabetes’. It’s just proper strength training with a few extra things I have to keep an eye on”
Medication still matters with type 2 diabetes
It would also be a mistake to assume that low blood sugar is purely a type 1 issue.
Some people with type 2 diabetes use insulin, while some glucose-lowering medications can also increase the risk of hypoglycaemia. Other commonly used medications work differently and have much less tendency to cause it.
So two people who both tell us they have type 2 diabetes may still need slightly different considerations around training.
This is why we ask about medication during the consultation rather than simply writing ‘type 2 diabetes’ on a health form and forgetting about it.
If somebody’s medication changes, we’d want to know about that too. How their glucose responds to exercise may change, particularly when insulin or medication associated with hypoglycaemia is involved.
The medical decisions remain with their GP, diabetes nurse or specialist team. Our job is to understand enough about the situation to make the training appropriate and worry-free.
Sometimes diabetes is part of something bigger
This is probably one of the most overlooked parts of training somebody with diabetes.
Not every case fits neatly into type 1 or type 2. There are other forms including LADA, some genetic forms of diabetes, steroid-induced diabetes and type 3c diabetes.
Type 3c is a particularly good example of why the wider medical picture matters. It develops following damage to the pancreas and can occur with conditions such as pancreatitis, cystic fibrosis, haemochromatosis or pancreatic cancer, or after surgery involving the pancreas.
In that situation, simply recording that somebody ‘has diabetes’ misses quite a lot of useful information.
The underlying pancreatic condition may affect digestion and nutrition as well as insulin production. For that person, the wider condition could actually have more influence on how we approach their training and diet than the word diabetes itself.
There can be similar considerations with the more common forms of diabetes. Type 1 diabetes is associated with a greater likelihood of some other autoimmune conditions. Type 2 diabetes can sit alongside high blood pressure, cardiovascular disease, kidney problems and other health issues.
Long-term diabetes can also lead to complications including peripheral neuropathy, kidney disease and diabetic eye disease.
If somebody has significant loss of sensation in their feet, for example, that’s useful information when deciding what activities are appropriate. If cardiovascular or kidney disease is also present, that may affect how we programme exercise. If somebody has been given specific exercise restrictions because of a diabetes-related complication, we work within those restrictions.
Sometimes diabetes is the main thing we need to think about, but sometimes it is only one part of the picture.
Mark B, DIABETES WITH ANOTHER CONDITION
“The diabetes wasn’t actually the thing I was most worried about when I came in, as mine is part of a wider condition called cystic fibrosis. It helped that we looked at everything together rather than treating me as simply ‘a diabetic client’.”
Do you need a special diabetes gym programme?
Usually, there isn’t a completely separate type of workout that suddenly becomes necessary because somebody has diabetes.
Once we understand how the condition is managed and whether there are any complications or other relevant medical issues, the principles of good training remain pretty normal.

Training with any condition, not just diabetes, doesn’t mean going easy or not being able to ‘train hard’. It just requires a little more thought.
We want to build strength progressively. We want to train the major muscle groups properly. We want enough work to cause an adaptation without doing far more than is necessary. We want people being physically active outside the gym as well as inside it.
And, as with anybody else, the programme should progress as their ability progresses.
Having diabetes doesn’t automatically mean spending six months lifting tiny dumbbells and being treated as fragile.
Somebody who has trained for years, manages their diabetes extremely well and understands exactly how their body responds to exercise may be considerably more capable than somebody without diabetes who hasn’t exercised for 20 years.
The diagnosis gives us useful information. It doesn’t tell us what somebody is physically capable of doing.
What dietary help can a personal trainer give someone with diabetes?
Nutrition is obviously relevant to diabetes, but there needs to be a sensible line between general nutritional coaching and clinical dietary advice.
There isn’t one universal ‘diabetic diet’.
For many people with type 2 diabetes, much of the useful advice looks remarkably similar to good nutritional advice generally. That might mean improving food quality, eating adequate protein and fibre, getting plenty of fruit and vegetables, being sensible with portion sizes and choosing an overall calorie intake appropriate to what they’re trying to achieve.
If losing weight is an appropriate goal, we can help somebody understand calorie intake, portion sizes and meal structure and find changes they can actually maintain. We can help them get enough protein while strength training, look at what they’re eating across the course of a normal week and identify relatively straightforward improvements rather than handing them an unnecessarily restrictive diet.
We can also help with the things that tend to decide whether a diet works in the real world: work lunches, weekends, takeaways, eating out, hunger, convenience and finding meals that somebody actually wants to keep eating.
Someone with diabetes doesn’t suddenly need to live on a diet of chicken, broccoli and brown rice.
There are, however, places where our advice stops.
With type 1 diabetes, carbohydrate counting and matching carbohydrate, insulin and activity are part of diabetes management. We aren’t going to prescribe insulin doses or tell somebody to alter them.
Likewise, someone considering a very low-calorie diet for type 2 diabetes remission should do that with appropriate healthcare support, particularly if medication may need adjusting.
If diabetes exists alongside kidney disease, coeliac disease, pancreatic disease, significant gastrointestinal problems or another condition that changes someone’s nutritional requirements, specialist dietary input may be appropriate.
Knowing when something needs referring elsewhere is part of doing the job properly, and we’re never afraid to say “not sure about that, I think you need to ask your doctor”.
Strength training can be part of managing diabetes
I’ve trained several people with diabetes over the years and currently have several clients with the condition.
There isn’t a single way that they all train.
Some need to keep a closer eye on their glucose around sessions. Some have other health conditions that influence their programme. Some want to lose weight. Others don’t. And with some, diabetes barely changes the exercises I would have chosen for them anyway.
That’s really the point.
We don’t have a ‘diabetes workout’. We find out what type of diabetes somebody has, how it is being managed, whether medication or insulin needs consideration, whether there are any complications or other medical conditions, what they can currently do and what they actually want to achieve. Then we build a proper training programme around the person.
If you have diabetes and you’re thinking about starting strength training in Nottingham, you’re welcome to come and talk it through with us. Tell us how your diabetes is currently managed, what guidance you’ve been given by your healthcare team and what you’d actually like to achieve from training.
From there, we can work out what sensible strength training looks like for you.
Frequently Asked Questions
Can you lift weights if you have diabetes?
For most people, yes. Current diabetes guidelines specifically include resistance training as a recommended form of exercise for people with both type 1 and type 2 diabetes. The individual considerations depend on the type of diabetes, medication, glucose response to exercise and whether there are any diabetes-related complications or other medical conditions.
Can you lift heavy weights with diabetes?
Having diabetes doesn’t automatically prevent someone from lifting heavy weights. What “heavy” means should be relative to the individual, just as it is for anybody else. Someone with well-managed diabetes and plenty of training experience may be perfectly capable of serious strength training. Any specific restrictions caused by complications or another health condition need to be taken into account.
Can strength training lower blood sugar?
Resistance exercise can improve glucose management and insulin sensitivity, particularly when it is performed regularly. The immediate blood glucose response varies, however. Glucose can fall during or after exercise, while some higher-intensity exercise can temporarily increase it. This is especially important for people using insulin or medication which can cause hypoglycaemia.
Is strength training good for type 2 diabetes?
Yes. Resistance exercise is recommended alongside aerobic activity for people with type 2 diabetes. As well as helping glucose management and insulin sensitivity, it helps maintain or increase muscle, improves strength and supports general health and physical function.
Does having type 1 diabetes change how you train?
It can change some of the management around a session rather than necessarily changing the exercises themselves. Insulin, carbohydrate intake, the timing and intensity of exercise and the individual’s usual glucose response all matter. Someone with type 1 diabetes should understand how to manage exercise through guidance from their diabetes team rather than relying on their personal trainer for insulin advice.
Should I tell my personal trainer that I have diabetes?
Yes. Your trainer should know what type of diabetes you have, how it is managed, whether you use insulin or medication which can cause low blood glucose, and whether you have any complications or related conditions that affect exercise. That doesn’t mean you need to be treated differently for the sake of it. It means your trainer has the information needed to coach you properly.
Can a personal trainer give dietary advice for diabetes?
A personal trainer can help with general healthy eating, calorie intake, protein, meal structure, weight management and making practical improvements to someone’s diet, provided they are suitably qualified to give that level of advice. Clinical diabetes nutrition management, insulin adjustment, therapeutic diets and complex dietary needs associated with other medical conditions should remain with the appropriate healthcare professionals.
Book your free Personal Training session today
If you’re in Nottingham and thinking about working with a personal trainer, this is the perfect opportunity to see what professional coaching can do.
Book your FREE personal training session and discover how expert guidance, a structured plan and genuine accountability can help you build strength, improve your fitness and achieve lasting results.
There’s no pressure and no hard sell. Just the opportunity to experience personal training for yourself, ask questions and see how we work.
After one session, you’ll know whether we’re the right gym, the right coach and the right approach for you.
Sign up to the RWF newsletter

